Jaw pain or soreness
Aching in front of the ear, along the jawline or in the cheek, often worse with chewing, yawning or talking at length.

TMJ & jaw pain · North Waterfront & Telegraph Hill
Jaw pain, clicking, locking and the headaches that come with them. Our chiropractors, licensed acupuncturists and dry needling specialists treat the joint and the muscles around it, without medication or surgery.
5.0 from 273 Google reviews · Mon to Fri, 8am to 6pm · No referral needed
Symptoms
TMJ problems rarely show up as jaw pain alone. Most people who come to us have two or three of these at once, and often have been told the cause is stress or a dental issue.
Aching in front of the ear, along the jawline or in the cheek, often worse with chewing, yawning or talking at length.
A click, pop or grating sound when you open or close. Noise on its own is common and not always a problem; noise with pain or catching is worth assessing.
The jaw catches, sticks, or will not open as far as it used to. Some people can no longer fit three fingers between their teeth.
Tension type headaches across the temples and forehead, often on waking, driven by the muscles that close the jaw.
The joint sits directly in front of the ear canal, so TMJ problems are often mistaken for ear infections.
Worn or sensitive teeth, a tired jaw in the morning, or a partner who hears grinding at night.
The jaw, neck and upper back share muscle and nerve connections. Jaw problems and neck problems travel together more often than not.
Cheeks and temples that feel tired or tight by the end of the day, sometimes with a change in how your bite feels.
The basics
The temporomandibular joint is the hinge that connects your lower jaw to your skull, just in front of each ear. You have two of them, and they work together every time you chew, speak, swallow or yawn.
Strictly speaking, TMJ is the name of the joint. The problem is a TMD, a temporomandibular disorder. Almost nobody searches it that way, so most clinics, including ours, simply say TMJ.
TMJ disorders fall into three broad groups, and plenty of people have more than one at the same time:
The encouraging part: most TMJ problems are muscle driven, and most improve with conservative care. Surgery is rarely the first answer and is not needed in the large majority of cases.
Choosing a provider
There is no single TMJ specialty, which is why this is confusing to search for. Several professions treat it from different angles, and the right starting point depends on what is actually driving your symptoms.
Treats the joint mechanics and the muscles around the jaw, neck and upper back. A sensible first stop when pain is muscular, when opening is restricted, or when jaw symptoms travel with neck pain and headaches. This is what we do here.
The right provider for your teeth and your bite. Dentists make the night guards and splints that protect teeth from grinding, and will spot a cracked tooth or decay that can masquerade as jaw pain.
A dentist with additional training specifically in TMJ and facial pain. Worth seeking out for complex, long standing or unexplained cases.
Involved when the bite itself or tooth alignment is a genuine contributor. Braces are not a routine TMJ treatment and should not be the first step for jaw pain.
For fractures, dislocations, significant structural damage and the small number of cases that do not respond to anything conservative. Surgery is a last resort, not an early one.
Manual therapy, jaw and neck exercise and posture retraining, with a great deal of overlap with what a chiropractor does for TMJ.
Uses acupuncture or dry needling for jaw and facial muscle pain and for the tension that often accompanies it. We have licensed acupuncturists on staff at 150 Lombard Street.
Worth seeing when ear pain, fullness or ringing is the leading symptom, to rule out an ear or sinus cause before treating the jaw.
Most people do best with more than one of these. A common and effective pairing is a dentist for a night guard to protect the teeth, plus hands on care to settle the muscles and restore movement.
The question we get most
Yes, for the right kind of TMJ problem. Since most TMJ pain is driven by the muscles that close the jaw and by restricted joint movement, hands on care aimed at both is a reasonable and low risk place to start.
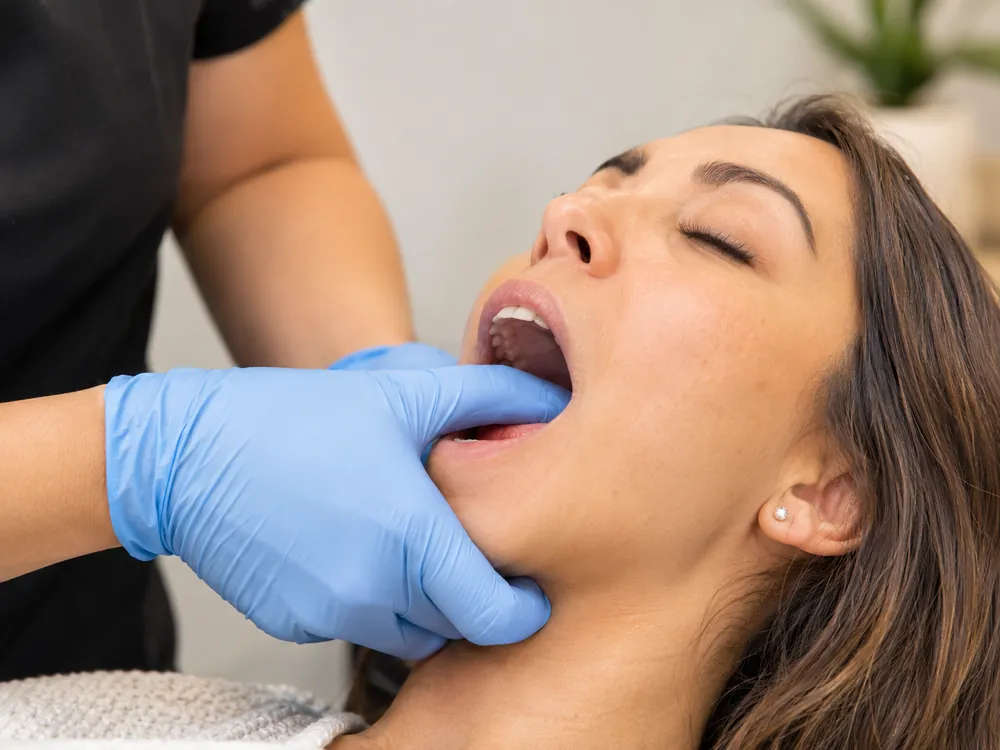
What that looks like in practice is work on the chewing muscles, gentle mobilisation of the jaw joint itself, treatment of the neck and upper back, and specific exercises you do at home between visits. Research on manual therapy and jaw exercise for TMJ is encouraging, though the studies are generally small, so we treat it as a sound first option rather than a guaranteed one.
Where a chiropractor is not the answer: a cracked tooth, decay, an abscess, a fractured or dislocated jaw, or a bite problem that genuinely needs dental work. We check for those, and if that is what we find, we tell you and send you to the right person.
If six to eight weeks of consistent conservative care has not moved your symptoms, that is a signal to escalate, not to keep going. We would refer you on to an orofacial pain specialist at that point.
What to expect
When it started, what makes it worse, whether it clicks or locks, how you sleep, how much you clench, and what dental work you have had. Most of the diagnosis comes from this conversation.
How far you open in millimetres, how far the jaw moves side to side, whether it deviates off centre on the way down, and where it is tender. These numbers give us something to re-test against.
Jaw symptoms and neck symptoms overlap constantly. Treating one and ignoring the other is the most common reason TMJ care stalls.
In plain English, including whether we think this is muscular, joint related or something that needs a dentist rather than us.
Along with two or three specific exercises to do at home. The home work matters more for TMJ than for almost anything else we treat.
Weighing your options
An honest map of what is available in San Francisco, including the things we do not provide. Conservative care is where almost everyone should begin.
Softer food for a spell, no gum, smaller bites, not opening wide, heat or ice, and easing the clenching habit during the day. Unglamorous and genuinely effective for a large share of cases.
Manual therapy to the jaw, neck and chewing muscles plus a specific home exercise programme. A common first step, and it works well alongside acupuncture or dry needling.
Fine needles for jaw and facial muscle pain, clenching tension and stubborn trigger points in the chewing muscles. Available from our licensed acupuncturists at 150 Lombard Street, on their own or alongside hands on care. Learn more about acupuncture and dry needling.
Made and fitted by a dentist. Protects the teeth from grinding and can settle morning jaw pain. We do not make these; we will tell you when we think you need one.
Anti inflammatories, short courses of muscle relaxants, and occasionally low dose tricyclics for persistent cases. Prescribed by your physician or dentist, not by us.
Steroid or platelet rich plasma injections, or flushing the joint. Reserved for specific joint problems that have not settled with conservative care, and delivered by a provider trained in the procedure.
Appropriate when the bite is genuinely a contributor. Not a routine answer to jaw pain, and expensive to pursue on the wrong indication.
Arthroscopy or open joint surgery for structural damage, significant degeneration, or cases that have failed everything else. A genuine last resort, and needed by very few people.
Jaw movement
Yes. Side to side movement, called lateral excursion, is a normal and necessary part of how you chew. People usually notice it for the first time when something feels uneven, and then start wondering whether it should be happening at all.
Most adults open 40 to 50mm between the front teeth, roughly the width of three stacked fingers. Under about 35mm counts as restricted.
Around 8 to 12mm in each direction, near enough a quarter of how far you open. Noticeably less on one side points to a restriction on that side.
Sliding the lower jaw forward, about 6 to 9mm. Often the first movement to be lost when the joint is irritated.
Grinding and clenching
Bruxism is grinding or clenching the teeth, and it is one of the most common drivers of TMJ pain we see. It happens in two distinct forms, and they are managed differently.
Sleep bruxism happens while you are asleep and you have no direct control over it. A dentist made night guard is the standard way to protect the teeth, and treating the muscles reduces the morning soreness that comes with it.
Awake bruxism is usually a daytime clenching habit tied to concentration or stress. This one responds well to awareness. The jaw should rest with lips together and teeth slightly apart. Most clenchers are surprised how rarely that is where their jaw actually sits.
Referred symptoms
The temporalis muscle fans across the side of your head, so when it is overworked from clenching the ache lands in the temples and behind the eyes. These are commonly treated as tension headaches or migraines for years before anyone looks at the jaw. If your headaches are worst on waking, the jaw is worth examining. See our headache page.
The joint sits immediately in front of the ear canal, which is why TMJ problems so often feel like an ear infection. Ear pain with a normal ear exam, fullness that does not clear, or ringing that changes when you move your jaw all point back to the joint. Get the ear itself checked first, then look at the jaw.
Jaw and neck problems travel together. The nerves that supply the jaw and the upper neck converge, and a head forward desk posture loads both. Treating the jaw while ignoring the neck is the usual reason progress stalls. See our neck pain page.
Where to find us
Two clinics a few minutes apart on the north waterfront, open Monday to Friday, 8am to 6pm. No referral is needed and we can usually see new jaw pain within a day or two.
Main clinic · North Waterfront
San Francisco, CA 94133
Monday to Friday, 8am to 6pm
Chiropractic care for the jaw and neck, Active Release Technique, Graston, laser therapy and your home exercise programme.
Telegraph Hill
San Francisco, CA 94111
Monday to Friday, 8am to 6pm
Acupuncture and dry needling for jaw and facial pain with our licensed acupuncturists.
Both clinics are an easy walk from Fisherman’s Wharf, North Beach, Russian Hill, Telegraph Hill and the Embarcadero, and a short ride from the Financial District, Nob Hill, Chinatown and the Marina.
Yes, for the kind of TMJ problem that is driven by muscle tension and restricted joint movement, which is the majority of cases. Treatment involves hands on work to the chewing muscles, gentle mobilisation of the jaw joint, care for the neck and upper back, and a home exercise programme. It is not the answer for a cracked tooth, an abscess, a fracture or a bite problem that needs dental work, and we will tell you if that is what we find.
There is no single TMJ specialty. If your pain is muscular, your opening is restricted, or your jaw symptoms come with neck pain and headaches, a chiropractor or physical therapist is a sensible first stop. If the problem is clearly dental, or you grind at night and need a guard, start with a dentist. For complex or long standing cases, an orofacial pain specialist is the right referral.
Often both, for different jobs. A dentist handles your teeth and your bite and makes the night guard that protects against grinding. A chiropractor treats the joint mechanics and the overworked muscles that produce the pain. Choose the dentist first if the trigger is clearly dental or you are grinding heavily at night, and the chiropractor first if the pain is muscular or travels into your neck and head.
It depends on your insurance and the care you need, so we check your benefits before your first visit rather than quote a number that turns out to be wrong. We work with many in network and out of network plans and offer payment plans. Call us on (415) 421-1115 and we will verify your coverage.
Yes. Side to side movement, called lateral excursion, is a normal part of chewing, and most adults manage around 8 to 12mm in each direction. What matters is whether it is even. Noticeably less movement one way, or a jaw that veers off centre and stays there, suggests one joint is not moving as it should.
Clicking usually means the small disc inside the joint is slipping out of position and snapping back as you open. On its own, in a jaw that opens fully and does not hurt, it is common and often needs no treatment at all. Clicking that comes with pain, catching or restricted opening is worth having assessed, because it can progress to locking.
If it is locked open or shut and you cannot move it, that is urgent and you should go to an emergency room or an oral surgeon the same day. If it catches intermittently but still releases, stop forcing it open, stay on soft food, apply heat, and get it looked at soon. Repeated locking tends to get worse rather than better when left alone.
It is a reasonable option for jaw and facial muscle pain, especially when clenching or stress is part of the picture. We have licensed acupuncturists at our 150 Lombard Street clinic who treat jaw pain, on its own or alongside hands on care. Results vary from person to person.
It can, especially for stubborn trigger points in the chewing muscles. A fine needle is placed into the tight band of muscle to release it. It is uncomfortable for a few seconds rather than painful. Our licensed acupuncturists provide dry needling at 150 Lombard Street, often as part of a broader plan.
If you grind in your sleep, a guard is the standard way to protect your teeth from wear, and it often reduces morning jaw soreness. It does not stop the grinding itself, which is why muscle treatment and managing daytime clenching still matter. Night guards are made and fitted by a dentist, not by us.
Yes to both. The temporalis muscle covers the side of the head, so when it is overworked the ache lands in the temples, which is why TMJ headaches are often mistaken for tension headaches. The joint also sits directly in front of the ear canal, so jaw problems commonly produce ear pain, fullness or ringing. Have the ear itself checked first, then look at the jaw.
Many people notice a change within two to three weeks, with most conservative plans running six to eight weeks. Jaw problems that have been there for years, or that involve genuine joint damage, take longer. If eight weeks of consistent care has not shifted your symptoms, that is a signal to escalate to an orofacial pain specialist rather than keep going.
We will measure how your jaw actually moves, work out whether this is muscular, joint related or something a dentist should handle, and start treatment the same day where it is appropriate.